Christopher Zoumalan, Oculoplastic Surgery

Reconstructive eyelid surgery

Ptosis Surgery Beverly Hills

You probably noticed it in a photograph first. One eye looks smaller, or the lid sits low enough that you lift your brow to see past it, and by evening your forehead aches from doing the eyelid’s job. Droopy eyelid surgery, or ptosis repair, raises the lid margin itself rather than removing skin above it.

Read more

Dr. Christopher Zoumalan measures lid height in millimeters before proposing anything. He is an ASOPRS fellowship-trained oculoplastic surgeon, board-certified in ophthalmology, with over 20 years of clinical experience dedicated to the eyelids. A millimeter low reads as unchanged. A millimeter high reads as startled.

20+ years of clinical experience9,000+ proceduresFeatured on The DoctorsNewsweek America’s Best Plastic Surgeons, 2023–2026

Find out in one unhurried appointment whether your eyelid or your skin is the problem.

The condition

What Is Eyelid Ptosis (Droopy Eyelid)?

Eyelid ptosis is an upper eyelid margin that sits too low. Eye surgeons measure it as MRD-1, the distance from the centre of the pupil to the lid margin. Normal is 4 to 5 millimetres; below 2, the lid blocks vision at the superior visual field.

Ptosis is not excess skin. Dermatochalasis drapes over the lash line and creates hooded eyelids without the lid margin being low; upper eyelid surgery treats that. Droopy eyebrows mimic both and call for a brow lift.

Mechanism decides the operation:

  • Involutional ptosis, or aponeurotic ptosis: the levator aponeurosis stretches from the tarsal plate with aging. The common adult form.
  • Congenital ptosis: present at birth; the levator muscle never develops normal strength.
  • Myogenic ptosis: a muscle disease such as myasthenia gravis.
  • Neurogenic ptosis: a nerve problem, including third nerve palsy and Horner syndrome.
  • Mechanical ptosis: weight on the lid, such as benign lesions or scarring.

Before and after

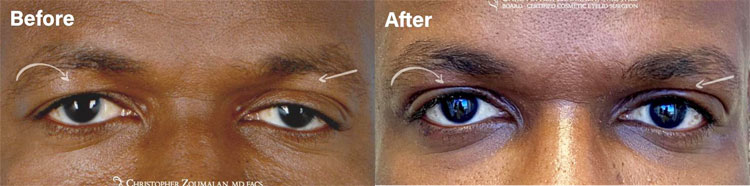
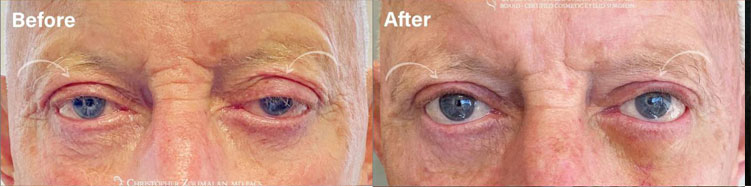
Ptosis Repair Before and After
Why Dr. Zoumalan

Why Choose Dr. Zoumalan for Ptosis Repair?

Ptosis surgery is measured in millimetres, which makes surgeon selection the variable patients control. A repair that lands a millimetre low reads as unchanged. A millimetre high reads as startled. That margin is where training shows.

  • Board certification: the American Board of Ophthalmology, and Fellow of the American College of Surgeons. The surgeon operating on your upper eyelid trained first on the eye underneath it, which is why dry eyes and lagophthalmos risk are assessed before technique is chosen.
  • Subspecialty training: ASOPRS fellowship in ophthalmic plastic and reconstructive surgery. No separate board certification exists in oculoplastic surgery; the fellowship is the recognised training for this field. It is a fair question to ask any surgeon you consult.
  • Experience: over 20 years of clinical experience and more than 9,000 eyelid procedures performed. Levator function varies from patient to patient, and volume is what turns technique choice into a measurement rather than a preference.
  • Exclusive focus: this practice is limited to the eyelids and orbit, not general facial surgery. Every operating day is spent on the same few millimetres of tissue.

The process

When Ptosis Surgery Is Medically Necessary

Upper eyelid ptosis is graded by how much visual field it costs, not by how it looks. When the lid margin crosses the pupil, ptosis repair restores sight. That makes it a functional problem, not a cosmetic issue.

Consultation

Levator function of the levator palpebrae superioris muscle drives every other decision. Dr. Zoumalan measures how far the lid travels between downgaze and upgaze, brow held still. Strong excursion points toward one repair, weak excursion another.

The exam records eyelid height, MRD-1, brow position, lower lid position and tear film quality, since dry eyes change candidacy. Prior photographs establish where your lids sat before.

The Procedure

  • Anesthesia: upper eyelid ptosis surgery is done under general anesthesia, with light or twilight sedation where needed. An outpatient procedure, 30 to 60 minutes per eye, same-day discharge.
  • Levator advancement: a hairline incision hidden in the eyelid crease. The surgeon shortens the stretched levator aponeurosis and reattaches it higher on the tarsal plate. A levator resection shortens the muscle itself and suits weaker lids. The standard external ptosis surgery for involutional cases.
  • Posterior approach: worked from inside the eyelid, no skin incision, no external scar. Dr. Zoumalan uses a variation on Müller muscle conjunctival resection (MMCR), shortening the superior tarsal muscle. A phenylephrine test predicts who responds.
  • Awake ptosis repair: patients stay conscious and comfortable without general anesthesia. Opening and closing the eye during surgery sets lid height and eyelid contour with the muscles working.

Recovery and Results

  1. Days 1 to 3: swelling and bruising peak. Cold compresses and an elevated head reduce both. Most report tightness, not pain.
  2. Week 1: dissolvable stitches or fine sutures come out at five to six days when external incisions were used. Blurry vision from ointment is common and settles.
  3. Weeks 2 to 4: back at desk work by day seven to ten, comfortable socially by week three.
  4. Months 1 to 3: final lid position and visual clarity declare themselves once swelling resolves. A levator repair typically lasts many years; recurrence is uncommon.

Millimetre symmetry is the hardest part of ptosis surgery. Dr. Zoumalan adjusts lid position roughly one week after surgery, in office, while the tissue still responds.

Individual results vary. Every procedure carries risk, including bleeding, infection, an asymmetrical result and worsened dry eye.

See what a millimetre of lid height actually changes before you decide anything.

Office Interior View

Candidacy

Ideal Candidates for Ptosis Surgery in Beverly Hills

  • Good candidates: adults whose upper eyelid margin shades the pupil, in stable health, with expectations measured in millimetres.
  • Functional candidates: patients whose superior visual field is measurably obstructed, reporting eye strain, headache and compensatory elevation. Untreated, severe upper eyelid ptosis costs real vision loss.
  • Congenital and pediatric: a lid covering the visual axis in early development stops the visual pathways forming normally. The result is amblyopia, the lazy eye later surgery cannot reverse. Pediatric ptosis with poor levator function calls for a frontalis sling, linking the eyelid to the forehead muscles. Severe cases are treated in infancy.
  • Medical considerations: contact lenses, prior eye surgery, genetics, injury and nerve damage account for most non-age-related cases. Myasthenia gravis, Horner syndrome, diabetes, stroke and thyroid eye disease can present as drooping eyelids, so the exam rules those systemic diseases out.
  • Not yet candidates: active dry eyes raise the risk of lagophthalmos, incomplete lid closure, after any lid-elevating procedure. Dr. Zoumalan does not operate on uncontrolled dry eye; your eye doctor manages that first.
  • Prior eye surgery: scarring changes tissue planes and closure mechanics. Those cases are handled as revisional eyelid surgery, starting from the prior operative report.

A consultation determines whether you are a candidate.

Combined treatments

Combining Ptosis Repair With Other Procedures

Ptosis rarely arrives alone. A second procedure in the same session means one anesthetic and one recovery.

Combined Eyelid Surgery

Ptosis correction surgery is frequently staged with skin removal in the same operation, meaning one recovery instead of two. Many ptosis patients carry excess eyelid skin, puffy eyes or sagging skin alongside the low lid margin.

Natural Looking Blepharoplasty®

Patients wanting a conservative cosmetic result alongside the repair ask about this technique, which preserves upper lid volume rather than hollowing it. The lid margin is raised and the natural fullness of the upper eyelid stays intact.

Asian Eyelid Surgery

East Asian lid anatomy allows ptosis repair to be combined with double eyelid surgery, where crease height and lid position are planned together rather than sequenced across two operations.

Cost and financing

Ptosis Surgery Cost and Financing in Beverly Hills

Cost depends on whether one or both eyelids are treated, which technique your anatomy requires, whether skin removal is combined with the repair, and anesthesia and facility fees. Send photographs and the office will give you a range over the phone. Your final price is set at consultation, once eyelid height and levator function have been measured, and it comes as one all-inclusive figure covering surgery, anesthesia and facility. PatientFi financing offers zero-interest payment plans.


Office Outdoor View

Book your consultation

Your Eyelid Ptosis Repair Consultation in Beverly Hills

Ptosis repair is one of the few eyelid procedures where the goal is measurable: a lid margin at the right height, matched side to side. This oculoplastic practice is limited to the eyelids and orbit, and the one-week adjustment gives residual asymmetry somewhere to go. Bring photographs from before your lids dropped; they are the most useful thing you can put on the table.

Bring your photographs and your questions to one unhurried appointment.

or call 310.278.4000

FAQ

Frequently Asked Questions About Eyelid Ptosis

How do I know if I have ptosis or excess eyelid skin?

Look at the eyelid margin, not the skin fold. If the lash line sits low against the pupil, that is eyelid ptosis. If the margin is normal but skin hangs over it, that is dermatochalasis. Lift your brow: if the heaviness clears, droopy eyebrows are involved.

What are the symptoms of ptosis?

A tired appearance, one eye looking smaller, a heavy upper eyelid by late afternoon. Functional signs matter more: trouble reading, driving at night, eye strain, headache, a habitually raised eyebrow. Some patients tilt the head back to see under the lid. Symptoms appearing suddenly warrant a neurologic workup.

How long does ptosis repair last?

A levator repair typically lasts many years. The tendon can stretch again with age, and a small share need a second adjustment. The one-week lid adjustment reduces the chance of residual asymmetry driving a revision.

Why does a droopy eyelid make my forehead ache?

When the eyelid stops lifting, the frontalis muscle in the forehead takes over. That compensatory elevation runs all day, and the ache is a common reason patients finally book. It settles once the lid margin is back where it belongs.

Can ptosis surgery be done at the same time as blepharoplasty?

Commonly, yes. When excess skin and a low lid margin coexist, upper blepharoplasty and ptosis repair are done in one session through the same eyelid crease incision, meaning a single recovery. Dr. Zoumalan determines at consultation whether your anatomy allows it.