Patient 4
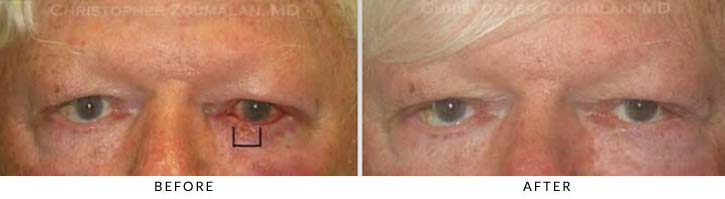
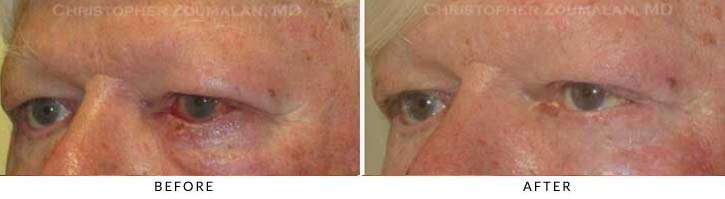
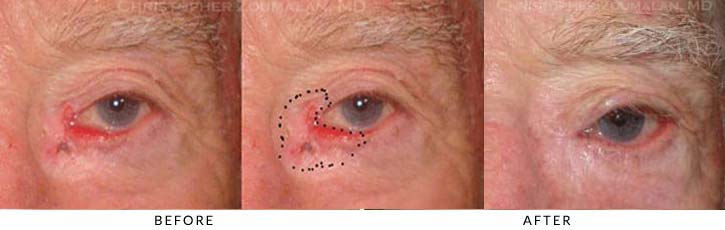
1) This patient had a recurrent squamous cell carcinoma of the left eyelid. It involved the medial (closest to the nose) portion of his upper and lower eyelid.
2) The surgical plan was to have the patient undergo a Mohs excision of the tumor by a Mohs-trained Dermatologist. The black outline depicts the area of resection that was necessary in order to clear the tumor and have clear (tumor-free) margins.
3) This photograph (top right) was taken 6 months after surgical repair. The patient had significant loss of tissue in the medial aspect of his eyelids and had to undergo two local skin and muscle advancement flaps to mobilize local tissue to close the defect. He also lost his tear ducts during the removal of the tumor but has since remained tumor free and very happy with the cosmetic results.
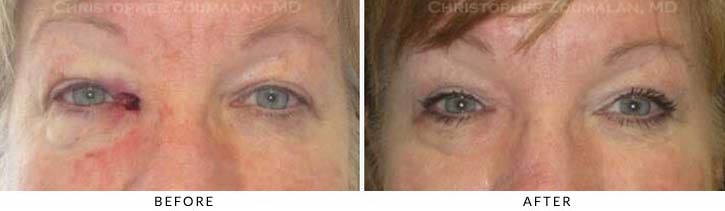
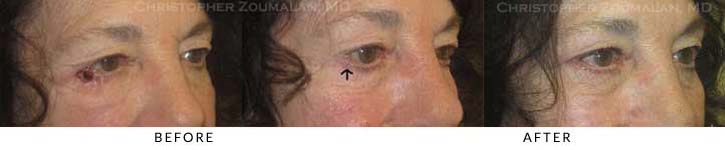
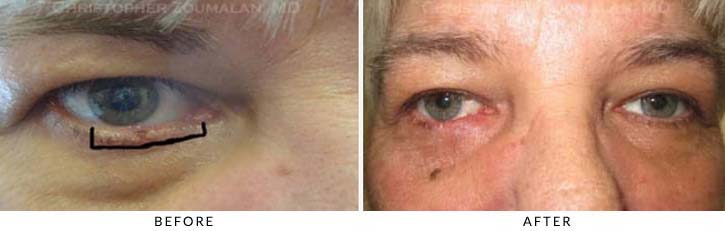
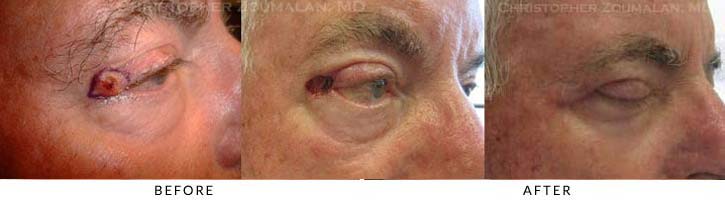
If it is a small defect, often local tissue can be rearranged or brought together to repair the eyelid. If it is a large defect like seen in the photo below, up to 80 percent of the lower lid is missing along with the tear duct system. In such instances, tissue from the upper lid is often needed to repair the defect through a procedure called a Hughes flap (aka tarsoconjunctival flap) named after one of the pioneers in Oculoplastic Surgery, Dr. Wendell Hughes. Tissue is taken from the upper lid as seen in this following photo and transferred in the lower lid. Unfortunately, the eyelid is sewn shut for at least one month until the flap takes place. A second surgery is then performed to “take down” the flap and allow for the eyelid to be reconstructed to a normal-appearing eyelid.